What the Anion Gap Indicates
This anion gap is a helpful way to interpret serum electrolytes and determine whether unmeasured ions may be altering acid-base balance. An Anion Gap Calculator typically relies on the major measured blood chemistry values, especially sodium, chloride, and bicarbonate, to help identify patterns that may suggest a metabolic disorder. In many clinical settings, the result is employed as part of an electrolyte panel rather than as a standalone diagnosis.
At its core, the anion gap shows the difference between positively charged and negatively charged components in the blood. Most calculators use serum sodium, serum chloride, and serum bicarbonate, while some also include potassium. Because potassium contributes less to the calculation in many routine methods, it may be excluded depending on the formula used. The goal is to calculate anion gap values that help clinicians detect hidden acids, unexpected proteins, or measurement issues.
Understanding the normal reference range matters because a value that appears “normal” in one context may be inaccurate in another. The anion gap is especially important when evaluating possible metabolic acidosis, but it also becomes relevant when the patient has a protein abnormality that can change blood chemistry. That is where clinical correlation becomes vital.
Why Hyperproteinemia Can Change Anion Gap Assessment
Hyperproteinemia refers to the fact that the blood contains a greater-than-normal amount of plasma proteins. This often involves increased globulins, albumin, or atypical proteins such as paraproteins. Because these proteins carry electrical charge, they can affect the interpretation of the anion gap even when the calculated number itself is unchanged.
Some proteins, especially negatively charged proteins, function as unmeasured anions. When plasma proteins rise, the body’s measured electrolytes may seem to shift in ways that affect the apparent gap. This is one reason a high protein level can complicate acid-base interpretation. A patient may have a result that looks unexpectedly low or normal, even when there is a true underlying acid-base disorder.
Albumin is the most important protein for this type of interpretation because it is a major unmeasured anion. Low albumin can lower the anion gap, but abnormal protein states can also distort the result through shifts in charge balance or by introducing paraproteins. In conditions such as multiple myeloma or monoclonal gammopathy, abnormal immunoglobulins may alter how the anion gap should be interpreted. In these cases, the number from an anion gap calculator should be viewed as one part of a larger diagnostic workup.
How an Anion Gap Calculator Works
An anion-gap equation is usually based on measured test results from the patient’s chemistry panel. The most common version is:
Anion gap = sodium - (chloride + bicarbonate)
Some methods include potassium as well, but many clinical calculators omit it for simplicity and consistency. The exact formula used matters because different labs and references may produce slightly different normal results.
The calculator uses serum sodium, chloride levels, and bicarbonate levels to estimate the gap between measured cations and measured anions. If the gap is high, it can suggest the presence of unmeasured acids. If it is low, it may signal hypoalbuminemia, hyperproteinemia, measurement interference, or another issue affecting the blood chemistry.
For practical use, the calculator should be paired with a review of the full electrolyte panel. A small change in sodium or chloride can alter the result, so the accuracy of the underlying laboratory values matters. The best way to calculate anion gap results is to interpret them in the context of the patient’s symptoms, other test results, and possible sources of error.
Adjusting the Anion Gap in Protein Abnormalities
As albumin heavily affects the anion gap, numerous clinicians use an albumin-corrected anion gap when protein abnormalities are present. This type of albumin correction serves to avoid overlooking a clinically important gap that is masked by low protein levels. It can also aid interpretation when protein patterns are atypical.
A more comprehensive protein correction may be considered when abnormal serum proteins such as paraproteins are thought likely. While albumin correction is the most established adjustment, some cases of hyperproteinemia require beyond a single correction step. This is especially true when results do not fit the clinical picture or when the reported value falls near the edge of the reference range.
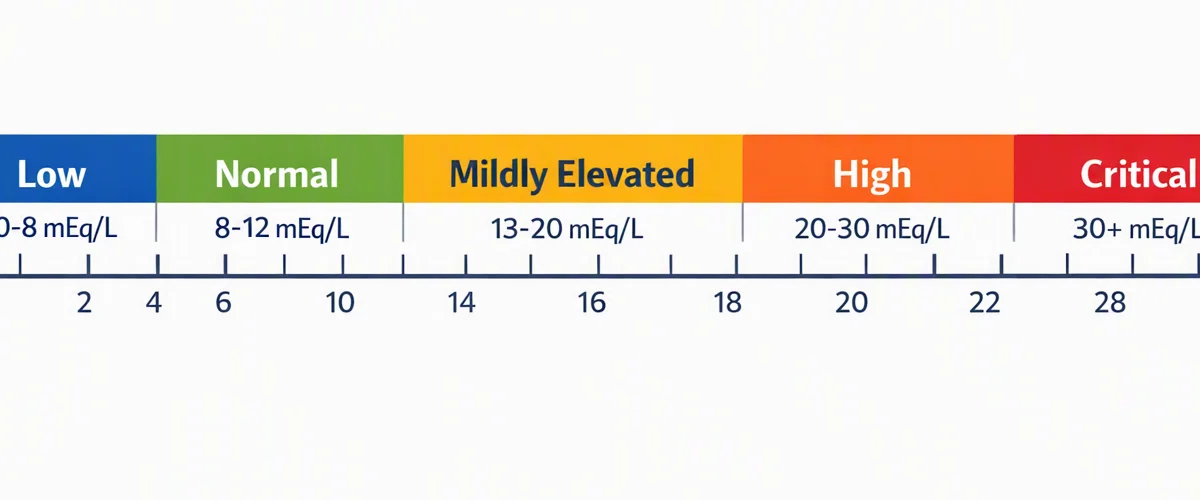
The corrected anion gap is not meant to replace clinical judgment. It is a tool that can improve acid-base interpretation and help explain why a result seems out of proportion to the patient’s condition. For example, a patient with low albumin may look as if they have a normal anion gap despite an underlying metabolic acidosis. Conversely, abnormal proteins can make the measured value harder to interpret. In those situations, the corrected anion gap can provide a more practical estimate than the raw number alone.
Frequent Causes of Elevated or Low Anion Gap
A high anion gap is often linked to retained acids and is commonly seen in metabolic acidosis. Problems including ketoacidosis, lactic acidosis, toxin exposure, and renal failure are classic causes. However, a high value is not the only abnormal pattern clinicians should recognize. A low anion gap can be just as important because it may suggest protein changes, lab error, or other hidden issues.
Hypoalbuminemia is one of the most common explanations for a low anion gap because albumin is a major unmeasured negative ion. When albumin falls, the anion gap often drops too. On the other hand, multiple myeloma and other plasma cell disorders can produce paraproteins that change the expected pattern. These abnormal proteins may lower the gap or make the result less reliable as a marker of acid-base status.
Lab artifact is another recurrent cause of an abnormal result. A falsely low chloride, incorrect sodium value, or sample handling issue can alter the calculated result. In some cases, the abnormality is not physiological at all but instead reflects measurement error or interference from the testing method. This is why an unexpected result should always trigger a review of the laboratory values and the testing context.
Working with the Calculator in Clinical Context
The best way to use of an Anion Gap Calculator is never mechanical calculation but careful clinical interpretation. A result should be considered alongside the patient’s symptoms, diagnosis, medications, and other serum proteins. A number alone cannot prove or exclude an acid-base disorder.
For example, a patient with vomiting, dehydration, or kidney dysfunction may show a changing electrolyte imbalance. Another patient may have a high protein state from chronic inflammation or a plasma cell disorder, which changes how the result is interpreted. In each case, the calculator provides a first step, but the interpretation depends on overall clinical correlation.
It also helps to ask whether the result matches the rest of the data. If the calculated anion gap suggests severe acidosis but the patient looks stable and the bicarbonate is only mildly reduced, the result may need a second look. Likewise, if a patient has known hyperproteinemia and an unexpectedly low gap, the number may reflect different protein chemistry rather than a true absence of unmeasured acids. This is why many clinicians use the calculator as part of a larger diagnostic workup rather than as a final answer.
Limitations of Anion Gap Calculation in Hyperproteinemia
There are important limits in diagnosis when using an anion gap calculator in the setting of hyperproteinemia. The calculation assumes that the main measured electrolytes are accurate and that unmeasured ions behave in expected ways. In reality, both assumptions can break down when proteins are abnormal.
One major issue is analytical interference. The selective electrode method used in many labs can be affected by unusual sample composition. High protein concentrations may alter the water fraction in plasma and influence how electrolytes are reported. This can produce pseudohyponatremia, in which the reported sodium level is artifactually low even though the physiologic sodium concentration is not truly reduced.
When pseudohyponatremia occurs, the calculated anion gap may be misleading. A seemingly low sodium can reduce the gap and create a wrong impression of a testing artifact related to acid-base status. In other cases, the issue is not sodium alone but a broader analytical error affecting the interpretation of blood chemistry. Because of these limitations, the calculator should never be used in isolation when hyperproteinemia is known or suspected.
When to Review Labs or Evaluate Further
Repeat testing is warranted when the anion gap result does not align with the clinical picture or when there is worry about a sample or analyzer problem. If the initial result is unexpected, a second chemistry panel can help confirm whether the change is real. This is especially helpful when the patient has known or suspected hyperproteinemia, because protein-related effects can change across assays and collection conditions.
Further evaluation often includes serum protein electrophoresis to assess for paraproteins or other abnormal protein patterns. This is an important step when multiple myeloma or monoclonal gammopathy is possible. In addition, checking kidney function can help clarify metabolic causes of an abnormal gap, including impaired clearance of acids or related solutes.
Blood gas analysis may be informative when the bicarbonate result is unclear or when there is concern about true acid-base disturbance. Blood gas testing can clarify whether the patient has a real metabolic acidosis or whether the chemistry panel is affected by a lab issue. If the pattern remains confusing, the clinician may need to review collection method, analyzer type, and the broader diagnostic workup before drawing conclusions.
FAQ About Anion Gap and Hyperproteinemia
How does hyperproteinemia affect the anion gap?
Hyperproteinemia can affect anion gap interpretation because excess plasma proteins, including globulins and paraproteins, can shift the balance of measured and unmeasured ions. The result may look unexpectedly low, normal, or otherwise inconsistent with the patient’s condition. That is why clinical correlation is important when reviewing the anion gap.
Do I need to correct the anion gap for albumin or other proteins?
In many cases, yes. An albumin-corrected anion gap is commonly used because albumin has a strong effect on the calculation. If there is a broader protein abnormality, a more individualized protein correction may be needed. The best approach depends on the available laboratory values and the suspected cause of the abnormal result.
May hyperproteinemia cause a low anion gap?
Indeed. A decreased anion gap can occur in hyperproteinemia, especially when abnormal proteins such as monoclonal proteins are present. It can also be seen with reduced albumin, https://anion-gap-calculation.com/causes/salicylate.html laboratory artifact, or measurement error. If the result is unexpected, it should be reviewed in context rather than assumed to represent a true physiologic change.
What lab tests can confirm the cause of an abnormal anion gap?
Common tests include a repeat electrolyte panel, SPEP, renal function studies, and sometimes arterial blood gas analysis. These tests help clarify whether the issue is related to metabolic acidosis, abnormal blood proteins, or a testing problem involving the electrode system. They also support a more complete clinical evaluation.
At what point should an abnormal anion gap be repeated or investigated further?
An abnormal result should be repeated when it does not fit the clinical picture, when there is concern for a sample problem, or when hyperproteinemia may have caused assay interference. Further investigation is warranted if the abnormality persists, especially if there is concern for myeloma, monoclonal protein disorder, or another serious metabolic disorder. In those situations, the anion gap calculator is a useful tool, but not the final step in laboratory interpretation.