What Is the Anion Gap?
The anion gap is a calculated result used in acid-base interpretation to help identify changes in electrolytes that may indicate an underlying acid-base disorder. It examines the major measured positive ions and negative ions in the blood, mainly sodium and chloride, along with serum bicarbonate in the calculation. Although it is not a direct measurement of a single substance, it gives a useful snapshot of electrolyte balance and overall serum chemistry.
Clinically, the anion gap helps uncover the presence of unmeasured anions or an anion deficit that may not be obvious from routine laboratory values. Because the blood must stay electrically neutral, any gap between measured cations and anions suggests that other ions are present but not directly listed on a standard electrolyte panel. That is why the anion gap is such a helpful diagnostic aid in reviewing acid-base problems.
What Makes the Anion Gap Matters in Acid-Base Interpretation
The anion gap matters because it helps differentiate metabolic acidosis into types that guide the differential diagnosis. In many cases, the first question is whether the patient has a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. This difference changes the clinical interpretation, next steps, and urgency of care.
In acid-base balance, the body relies on a closely regulated buffer system involving bicarbonate, lungs, and kidneys. When acid builds up or bicarbonate is lost, the acid-base balance moves. The anion gap helps determine whether that shift is due to increase of acids that create unmeasured anions or due to direct bicarbonate loss with compensatory chloride retention.
In practice, the anion gap is part of broader clinical interpretation. It should not be used alone. Instead, it is interpreted with symptoms, blood gas data, the electrolyte panel, and the overall clinical picture. That combined approach helps avoid missed diagnoses and improves the accuracy of acid-base interpretation.
How an Anion Gap Calculator Works
An anion gap calculator is a simple tool that uses a common formula to estimate the gap from routine laboratory values. Most calculators need serum sodium, serum chloride, and serum bicarbonate. Some versions also incorporate albumin so they can deliver a corrected anion gap.
The core logic is straightforward: sodium is the main measured cation, while chloride and bicarbonate serve as major measured anions. The calculator compares these values to assess the amount of unmeasured ions in the blood. This makes it a quick diagnostic aid when assessing a patient’s electrolyte panel or serum chemistry.
Using an anion gap calculator can help clinicians and learners rapidly spot whether the result points to a metabolic problem. It is especially helpful when assessing metabolic acidosis, because the gap may point toward lactate, ketones, toxins, or kidney-related acid retention. The calculator does not substitute for judgment, but it makes interpretation more streamlined.
Anion Gap Formula and Normal Ranges
The usual anion gap formula can be written as:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Certain labs rely on slightly different formulas or reference approaches, but the concept is identical. The result is then measured against the lab’s reference range. A typical normal anion gap is often around 8 to 12 mEq/L, though the exact range varies by the laboratory and measurement method.
Because the normal range can vary, it is important to interpret the number using the local reference range rather than a single universal cutoff. The presence of albumin also affects the expected result. Since albumin is a negatively charged protein, lower levels can make the anion gap appear falsely low unless an albumin adjustment is used.
In other words, a “normal” result is not always truly normal. Understanding the formula, the lab’s reference range, and the effect of albumin can make the calculation more accurate and clinically useful.
How to Understand a Increased Anion Gap
A high anion gap metabolic acidosis indicates that acids are piling up in the body and resulting in unmeasured anions. This is often the first clue to serious illness. Typical causes include lactic acidosis, ketoacidosis, renal failure, and certain poisonings.
Lactic acidosis develops when lactate builds up due to poor perfusion, shock, severe infection, seizures, or other problems that impair oxygen delivery or utilization. Ketoacidosis may occur in diabetes, starvation, or alcohol-related states, where ketones become the dominant acids. In both settings, the body’s buffer system is overrun, and the anion gap rises.
Renal failure can also result in a high gap because the kidneys cannot excrete acid efficiently, causing retention of acids and unmeasured anions. This makes kidney function an key part of the differential diagnosis.
When the anion gap is high, the interpretation should focus on the likely source of acid production or impaired clearance. The calculator can help identify the problem, but the cause still needs clinical correlation with history, medications, symptoms, and lab testing.
How to Read a Normal Anion Gap
A normal anion gap metabolic acidosis usually means the body is depleting bicarbonate or gaining chloride, rather than accumulating a large amount of unmeasured acid. In this context, the total gap stays within the reference range even though the patient still has a clear acid-base disorder.
Common causes include bicarbonate loss from diarrhea and abnormal renal acid handling from renal tubular acidosis. These conditions often lead to a hyperchloremic pattern, where the chloride level rises as bicarbonate falls. That pattern keeps the anion gap fairly stable while the bicarbonate level declines.
Recognizing this pattern matters because a normal anion gap does not rule out serious disease. A patient with severe diarrhea or renal tubular acidosis can still be significantly acidotic. In these cases, the anion gap calculator supports the broader clinical interpretation by showing that the acid-base disorder is present even if the gap is not elevated.
Albumin Compensation and Its Effect on the Result
Serum albumin is one of the key unmeasured anions in blood. When low albumin is present, the calculated anion gap may be decreased than expected because there are less negatively charged proteins contributing to the gap. That is why albumin compensation is so important.
A corrected anion gap adjusts the result to match the patient’s albumin level. This helps avoid missing a true high-gap disorder in someone with low protein levels. In clinical terms, the correction improves assessment and reduces false reassurance.
Albumin adjustment is especially useful in hospitalized patients, those with chronic illness, malnutrition, liver disease, or inflammatory conditions. In these settings, low albumin can mask a clinically important increase in the gap. Using a corrected value improves the accuracy of acid-base assessment and helps reveal whether hidden acids are present.
Because albumin is a major protein in serum, even moderate changes can affect the result. A calculator that includes albumin correction is often more helpful than a basic formula alone.
Frequent Causes of Anion Gap Abnormalities
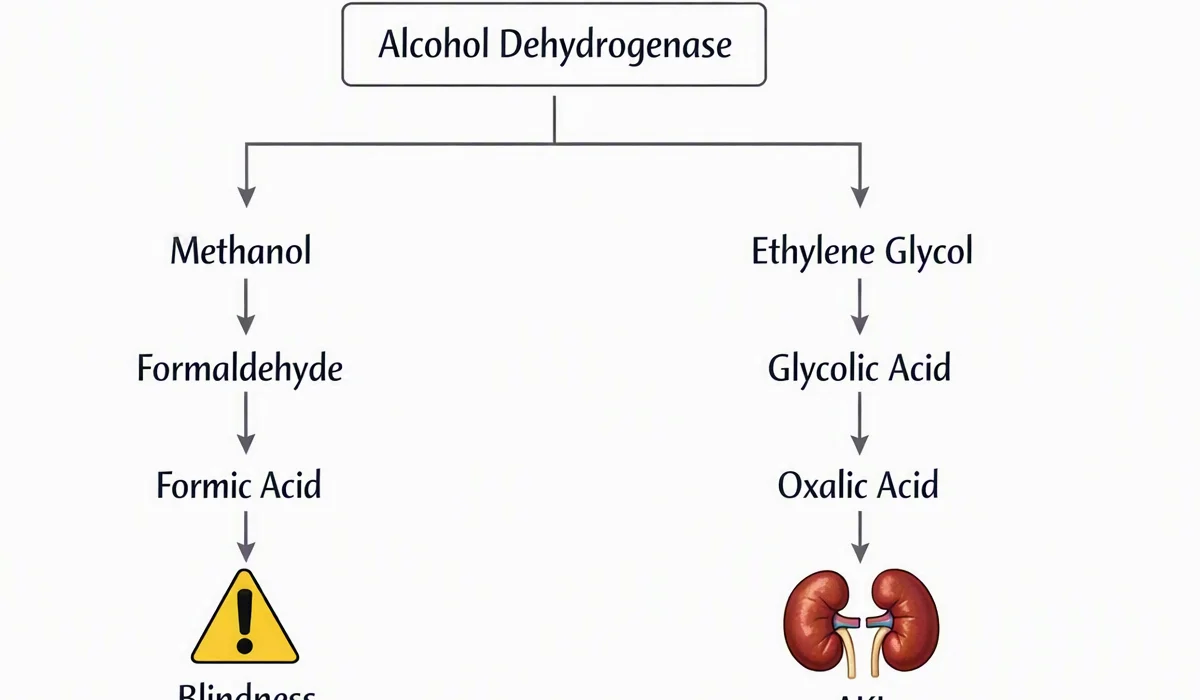
A number of conditions can alter the anion gap, and a thorough differential diagnosis is important. Causes of high-gap acidosis often include toxins, uremia, and severe metabolic stress. Other notable examples include salicylates and ethylene glycol.
Uremia from advanced kidney dysfunction can increase retained acids and raise the gap. Salicylates may cause a complex acid-base picture, sometimes with a mixed disorder, so the anion gap is only one part of the assessment. Ethylene glycol exposure is a toxic ingestion that can cause severe high-gap acidosis, often with additional clues on blood testing and clinical history.
Low or normal gap abnormalities are also important. These often reflect bicarbonate loss, chloride gain, or albumin changes rather than an accumulation of MUDPILES high anion gap classic organic acids. The key is not only to calculate the number but also to relate it to the patient’s presentation, medication list, renal function, and possible toxic ingestion.
Stepwise Example Calculations
Here is a simple worked example using common lab values:
- Sodium: 140 Chloride: 102 Bicarbonate: 24
Applying the formula:
Anion gap = 140 - (102 + 24) = 14
If the lab’s reference range is 8 to 12, this result is mildly elevated. Depending on the clinical context, the patient may need further evaluation for incipient high-gap metabolic acidosis, mild ketosis, lactate elevation, or another cause of increased unmeasured anions.
Consider a second example:
- Sodium: 138 Chloride: 110 Bicarbonate: 18
Anion gap = 138 - (110 + 18) = 10
This result is within a typical reference range, but the low bicarbonate indicates acidosis. That pattern suggests normal anion gap metabolic acidosis, which should prompt evaluation for diarrhea, renal tubular acidosis, or other sources of bicarbonate loss.
These examples show how a calculator can support interpretation by linking serum sodium, serum chloride, and serum bicarbonate to the broader clinical context.
Limitations and Common Mistakes
Even a reliable anion gap calculator has constraints. One common mistake is assuming the result alone proves a diagnosis. The gap is a hint, not a final answer. A second issue is laboratory error, which can affect the calculation if one of the input values is inaccurate.
Another significant mistake is missing a mixed acid-base disorder. For example, a patient can have a high-gap acidosis and a concurrent metabolic alkalosis or respiratory disorder that makes the numbers harder to interpret. In these situations, reliance on the calculator alone can lead to misclassification.
Albumin effects are also frequently overlooked. Without albumin correction, a clinically important high-gap disorder may be missed in a patient with hypoalbuminemia. In short, the calculator is most useful when combined with clinical context, a blood gas, and careful review of the full chemistry panel.
When to Seek Clinical Evaluation
An unexpected gap should be interpreted alongside the patient’s symptoms and overall condition. Signs such as rapid breathing, confusion, vomiting, dehydration, severe weakness, chest discomfort, or altered mental status may require prompt evaluation. A blood gas can help confirm the severity of the acid-base problem and show whether compensation is present.
Additional concern is warranted when there are significant electrolyte abnormalities, suspected toxic ingestion, worsening kidney function, or evidence of severe acidosis. Because metabolic acidosis can progress quickly, some patients need urgent care rather than routine follow-up.
When an abnormal result appears with concerning symptoms, the anion gap calculator should be treated as a first step, not the endpoint. The next step is a full clinical evaluation that may include repeat labs, toxicology testing, renal studies, and a more detailed acid-base assessment.
FAQ
What does anion gap calculator measure?
An anion gap calculator determines the gap between measured cations and measured anions in the blood. It uses serum sodium, serum chloride, and serum bicarbonate to spot unmeasured anions and support acid-base interpretation. It is a useful diagnostic aid for detecting metabolic acidosis and related disorders.
What is a normal anion gap range?
A standard reference range is generally about 8 to 12 mEq/L, but the exact normal anion gap depends on the laboratory and method used. Always interpret the result using the local lab’s reference values and consider whether albumin may be lowering the apparent gap.
How do you correct the anion gap for albumin?
Albumin correction raises the result upward when hypoalbuminemia is present, because low albumin can hide a true elevation. The exact formula may differ, but the goal is the same: to derive a more accurate corrected anion gap that reflects the patient’s true acid-base status.
What can cause a high anion gap metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and toxic ingestions such as salicylate poisoning and ethylene glycol poisoning. These conditions increase acids or unmeasured ions, leading to a high anion gap metabolic acidosis.
Can a normal anion gap still indicate a serious acid-base disorder?
Yes. A normal anion gap metabolic acidosis can still be clinically significant and may occur with diarrhea or renal tubular acidosis. The gap may stay normal because the problem is usually bicarbonate loss rather than accumulation of new acids, so the blood still shows a meaningful acid-base disorder.