What exactly is Starvation Ketoacidosis?
starvation ketoacidosis is a kind of metabolic acidosis that appears when the body gets insufficient enough carbs or overall energy intake and begins relying heavily on fat for fuel. This shift leads to ketosis, a state in which the liver produces ketone bodies to supply energy. When this process becomes stronger, acid production increases enough to disrupt acid-base balance and shift laboratory values.
The trigger is usually fasting, prolonged poor intake, or malnutrition. In these cases, the body experiences an energy deficit and a gradual drop in circulating glucose availability. As glucose availability drops, the body increases fat metabolism, which raises ketoacid production. This is different from everyday short-term ketosis because starvation states can produce a clinically meaningful acid-base disturbance.
Starvation ketoacidosis often occurs when nutritional deprivation is severe enough that the liver generates more acidic byproducts than the body can easily buffer. The main ketone-related acids are beta-hydroxybutyrate and acetoacetate. These compounds are part of normal ketone physiology, but in excessive amounts they contribute to metabolic derangement and a recognizable pattern of high anion gap metabolic acidosis.
Understanding this process matters because not all ketosis is the same. In starvation ketoacidosis, the key issue is not simply the presence of ketones, but the combination of glucose depletion, acid generation, and the resulting change in laboratory interpretation. That is why the Anion Gap Calculator can be valuable as a quick tool for clinical interpretation of the lab pattern.
How Starvation Ketoacidosis Raises the Anion Gap
The anion gap goes up when acids build up in the blood and their charged components are not directly measured in a standard electrolyte screen. In starvation ketoacidosis, the major cause is the buildup of unmeasured anions generated from ketone bodies. As beta-hydroxybutyrate and acetoacetate rise, they use up buffering capacity and leave behind negatively charged acid metabolites that increase the gap.
This is the classic mechanism of a high-gap acidosis. The body answers to acid buildup by lowering bicarbonate, which is the primary buffer consumed during acidosis. As bicarbonate falls, the gap often increases because the lost buffer is functionally replaced by acidic anions that are not directly reflected in routine chemistry values.
The process is driven by ketone accumulation during prolonged fasting or nutritional deprivation. When insulin levels are relatively low and glucose intake is insufficient, the body shifts toward ketone production for fuel. This adaptive response becomes harmful when ketone generation outpaces utilization and elimination. The resulting organic acids disrupt acid-base balance and produce the elevated anion gap seen on labs.
Although both ketone bodies contribute, beta-hydroxybutyrate is often the dominant acid in more significant ketoacid states. Acetoacetate also increases the measured acid load, but the total burden depends on severity, duration, and physiologic stress. The important point is that the ketones function as organic acids, and their presence explains why starvation ketoacidosis is a true cause of anion gap calculation abnormalities rather than a benign lab curiosity.
Put simply: starvation produces an energy shortage, the body burns fat, fat metabolism yields ketones, and those ketones act as unmeasured acids. That chain of events is why the anion gap rises.
How to Calculate and Analyze the Anion Gap
An Anion Gap Calculator may help estimate whether the electrolyte pattern suggests a increased-gap acidosis. The standard calculation uses sodium, chloride, and bicarbonate:
Anion gap = sodium - (chloride + bicarbonate)
This calculation is easy to use, but how you interpret it depends on the full clinical context. A higher-than-expected result may indicate excess unmeasured anions, while a typical result makes starvation ketoacidosis less probable or may reflect an initial / less severe stage. Since laboratory reference ranges differ, the exact cutoff should be evaluated with the laboratory-specific values and the patient’s whole clinical picture.
In starvation ketoacidosis, the gap increases because bicarbonate is used up buffering the acids generated by ketogenesis. The low bicarbonate often tracks the degree of acidosis. Meanwhile, chloride may seem relatively normal or may rise in mixed patterns depending on volume status and replacement fluids. Sodium is necessary for the calculation and may also vary with dehydration, poor intake, or concurrent illness.
When using an Anion Gap Calculator, it is useful to think in terms of clinical interpretation rather than a single value. A modestly elevated gap may still be important if the patient has clear starvation, vomiting, poor intake, or visible ketosis. A extremely high value suggests a more severe metabolic acidosis or another concurrent cause of high anion gap metabolic acidosis.
To interpret the result effectively, combine the gap with the rest of the laboratory results:
- Sodium: helps ground the overall calculation and assess hydration or dilutional effects. Chloride: helps show whether the acidosis is accompanied by secondary or mixed changes. Bicarbonate: typically decreases as acid load increases and is a key marker of disease intensity.
The result is merely a single part of the puzzle. The aim is not only to identify an out-of-range result, but to link it to the pattern of ketosis, pH disturbance, and the likely cause of the metabolic derangement.
Characteristic Lab Findings in Starvation Ketoacidosis
Starvation ketoacidosis has a well-known laboratory pattern, although the exact presentation varies depending on the length of fasting, degree of malnutrition, and any underlying illness. The most helpful tests often include serum glucose, electrolytes, arterial blood gas, and serum ketones.
Serum glucose is commonly normal or low rather than markedly elevated. One of the main clues separating starvation ketoacidosis from other forms of ketoacidosis. Because the underlying problem is insufficient intake rather than excess glucose, the glucose level may reflect exhaustion rather than hyperglycemia.
Electrolytes often show the biochemical signature of acid-base stress. The bicarbonate level is usually low, supporting the diagnosis of metabolic acidosis. Sodium and chloride may vary depending on fluid losses, vomiting, dehydration, or treatment before testing. Reviewing the full panel of serum electrolytes helps determine whether the picture is isolated or mixed.
Serum ketones are typically positive, and if quantitative testing is available, elevated beta-hydroxybutyrate supports the diagnosis more strongly than a basic urine ketone screen alone. This is because urine ketone testing may underrepresent the burden of beta-hydroxybutyrate. In starvation states, beta-hydroxybutyrate can be disproportionately elevated and is a major driver of the acid load.
An arterial blood gas may show acidemia with a low bicarbonate and compensatory respiratory changes. A patient may develop compensatory hyperventilation as the body tries to lower carbon dioxide and offset the acid load. This respiratory response helps maintain pH, but it does not correct the underlying problem.
Findings often include:
- Low or normal serum glucose Low bicarbonate Positive serum ketones Elevated beta-hydroxybutyrate and acetoacetate Abnormal electrolytes Acid-base changes on arterial blood gas
These findings support the diagnosis, but they also help estimate severity. The more pronounced the acidosis and ketone burden, the more likely the anion gap is to be clearly elevated.
How It Differs From Against Diabetic Ketoacidosis and Other Causes
Starvation ketoacidosis can appear similar to other sources of high anion gap metabolic acidosis, so distinguishing it from related conditions is important. The closest mimic is diabetic ketoacidosis, but there are several distinctions.
In diabetic ketoacidosis, the core issue is insulin deficiency, which triggers severe ketone production and usually produces https://anion-gap-results755.tearosediner.net/what-is-the-equation-for-anion-gap significantly higher glucose levels. Starvation ketoacidosis, by contrast, is driven by glucose depletion and inadequate intake. The patient may have usual or low glucose rather than marked hyperglycemia. That distinction changes both the diagnostic thinking and treatment priorities.
Alcoholic ketoacidosis is another notable differential. It often occurs after poor intake combined with heavy alcohol use and may share features of starvation physiology. Like starvation ketoacidosis, it can produce ketone-related acids and an elevated anion gap. The broader context, however, differs, and alcohol use can add further metabolic complexity.
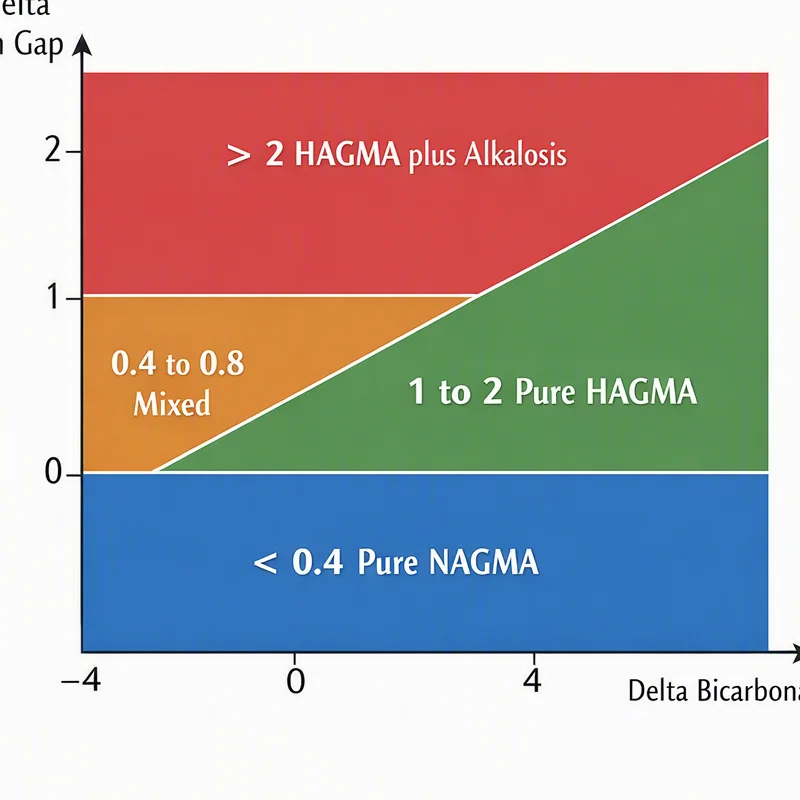
Lactic acidosis is another major cause of high anion gap metabolic acidosis. Instead of ketone bodies, lactate is the main unmeasured anion. Lactic acidosis may occur with tissue hypoperfusion, sepsis, or other forms of metabolic stress. If lactate is elevated, it can explain part or all of the gap, even if ketosis is present at the same time.
Renal failure can also raise the gap because failing kidneys cannot clear acids effectively. In that setting, retained acids and other retained solutes contribute to the anion gap. Renal impairment can coexist with starvation or dehydration, which makes interpretation more difficult and reinforces the need for careful diagnostic evaluation.
The key differences often come down to the pattern of labs and the clinical story:
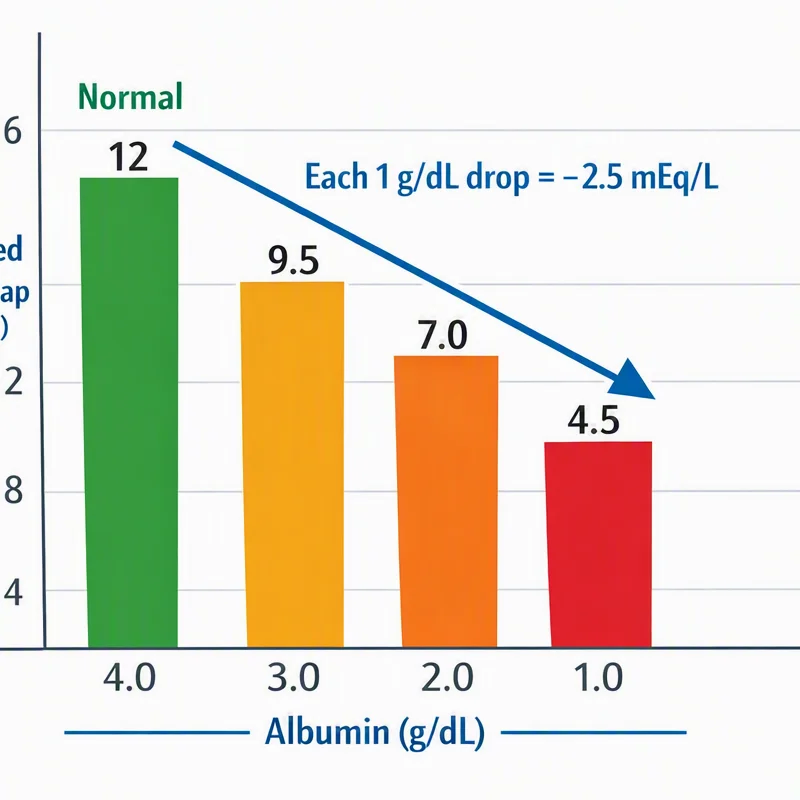
- Diabetic ketoacidosis: usually marked hyperglycemia and insulin deficiency Starvation ketoacidosis: fasting, malnutrition, low or normal glucose, ketone-driven acidosis Alcoholic ketoacidosis: alcohol use plus poor intake, overlapping metabolic features Lactic acidosis: elevated lactate from hypoperfusion or stress Renal failure: impaired acid clearance and retained metabolic acids
Because these conditions can overlap, the best approach is to use the anion gap as a first step, not the final diagnosis. The gap identifies the presence of excess unmeasured anions, but only the rest of the clinical picture can identify the cause.
When a High Anion Gap Needs Urgent Evaluation
A elevated anion gap always requires care, but the level of concern depends on the severity, associated symptoms, and the overall acid-base disorder. Starvation ketoacidosis may be slight in some cases, but it can still become dangerous if the patient is fluid depleted, not able to eat, or has another illness adding to the metabolic disturbance.
Prompt evaluation is essential when symptoms suggest progressive acidosis or systemic illness. These may include mental status changes, significant weakness, persistent vomiting, rapid breathing, dehydration, or inability to keep down intake. A patient with clear acidemia on an arterial blood gas and an elevated gap needs prompt clinical assessment rather than simple observation.
The concern is not only the ketones themselves, but the overall acid-base balance. If bicarbonate continues to decline, the acidosis can worsen. If the patient has concurrent infection, vomiting, renal impairment, or significant volume depletion, the metabolic picture can worsen quickly.
Useful considerations during assessment include:
- How long the patient has had reduced intake or fasting Whether there is malnutrition or ongoing lack of adequate nutrition Evidence of ketosis or high ketone burden Whether serum glucose is low, normal, or elevated Whether another cause of high anion gap metabolic acidosis may also be present
If the patient is symptomatic or the laboratory values show a substantial metabolic derangement, the issue should be treated as beyond a simple electrolyte abnormality. The elevation in the anion gap is a marker of underlying acid production, and the source for that acid load must be identified.
Common Questions About ketoacidosis from starvation and Anion Gap
Does ketoacidosis from starvation always cause a raised anion gap?
Not always, but it often does. Starvation ketoacidosis typically increases the anion gap because ketone-related acids generate unmeasured anions. In mild or mild cases, the gap may be only mildly increased or even appear almost normal if the acid load is minimal or if other electrolyte changes are present. The overall clinical context and anion gap interpretation are important as much as the number itself.
How elevated is the anion gap in starvation ketoacidosis?
The level of elevation differs with the severity of ketosis, duration of fasting, and presence of other illnesses. Some cases show a modest rise, while more severe starvation ketoacidosis can produce clear high anion gap metabolic acidosis. The exact level is less important than whether the result aligns with the rest of the picture, including bicarbonate, serum glucose, and ketone testing.
Which lab tests are useful to confirm fasting ketoacidosis?
The most helpful tests include serum glucose, electrolytes, arterial blood gas, and serum ketones. Quantitative beta-hydroxybutyrate is especially helpful because it reflects the main ketone burden more precisely than some urine tests. These results, combined with the history of reduced intake or malnutrition, support the diagnosis.
What makes starvation ketoacidosis different from diabetes-related ketoacidosis?
Diabetic ketoacidosis is driven by insulin deficiency and usually presents with markedly elevated glucose levels. Ketoacidosis from starvation is caused by glucose depletion from inadequate intake and often has typical or low serum glucose. Both can produce ketosis and elevated anion gap acidosis, but the trigger, lab pattern, and treatment approach differ.
Can the anion gap go back to normal after therapy?
Yes. As the underlying cause is corrected, ketone production falls, unmeasured anions decrease, and the anion gap can come back toward typical values. Care usually addresses the energy deficit, fluid replacement, and electrolyte abnormalities, which helps reestablish acid-base balance. Follow-up laboratory values are often used to show improvement in metabolic acidosis and overall clinical status.
Starvation ketoacidosis is a genuine acid-base disturbance, not just a simple ketotic state. The key pattern is the rise in the anion gap from ketone-related organic acids, especially beta-hydroxybutyrate and acetoacetate, during periods of fasting or malnutrition. An Anion Gap Calculator helps you identify that pattern efficiently, but the most reliable interpretation always comes from pairing the calculation with the clinical story, laboratory values, and thorough medical assessment.