What Is the Anion Gap?
The anion gap is a derived value used to assist interpret an electrolytes panel and recognize an underlying acid-base disorder. It contrasts the major measured positive ions in blood, mainly sodium, with the major measured negative ions, especially chloride and bicarbonate. Because the body contains many other charged particles that are not directly listed on a routine serum chemistry report, the anion gap acts as a diagnostic clue for those unmeasured ions and unmeasured anions.
At a practical level, the anion gap helps clinicians see whether a low serum bicarbonate reflects true acid buildup or a different process affecting acid-base balance. That makes it an essential part of a broader electrolyte panel and clinical interpretation. It is not a standalone diagnosis; it is a pattern that guides further evaluation.
The key idea is simple: the blood has to maintain acid-base balance within a narrow reference interval. When acids accumulate, bicarbonate often falls as it buffers those acids. The resulting change may or may not increase the anion gap, depending on which ions are present and whether there is a shift in chloride or other electrolytes.
Why Bicarbonate Matters in Acid-Base Balance
Bicarbonate is among the body’s main buffers. As part of the buffer system, it helps resist abrupt fluctuations in blood pH by buffering excess acid. This buffering capacity is central to normal physiology, and it clarifies why bicarbonate is so important in acid-base analysis.
If acid is added to the bloodstream, bicarbonate may be used up during buffering. That can produce bicarbonate depletion, which is why a low bicarbonate value is often a important sign in metabolic acidosis. However, low bicarbonate is not a diagnosis by itself. It is a lab result that needs context from the rest of the chemistry panel and, often, an arterial blood gas.
Bicarbonate matters in two ways. To begin with, it is a biologic buffer. Next, it is part of the anion gap calculation formula. Because it is subtracted from sodium together with chloride, changes in bicarbonate directly influence the derived gap. That is why changes in bicarbonate can show whether the body is losing bicarbonate, retaining acid, or adjusting for another disorder.
In many cases, the anion gap reflects a balance between acid production and the body's response through the buffer system and metabolic compensation. A rising gap often indicates the accumulation of acids that leave behind acid retention in the form of unmeasured ions. A falling bicarbonate, therefore, is both a physiologic response and a piece of the calculation.
In what way the Anion Gap Is Calculated
An Anion Gap Calculator uses a basic formula to routinely measured electrolytes. The standard version is:
Anion gap = sodium − (chloride + serum bicarbonate)
Some versions also include potassium, though many standard interpretations do not. A potassium-inclusive formula may be written as sodium + potassium − (chloride + bicarbonate). In general practice, the potassium-free version is often used because the contribution of potassium is limited relative to sodium.
The key point is that serum bicarbonate is not just a background number. It is a core part of the calculation. If bicarbonate falls and chloride does not rise enough to offset it, the anion gap will increase. If bicarbonate falls while chloride rises proportionally, the gap can stay within range.
This is why an Anion Gap Calculator is helpful as a quick interpretation aid. It links the basic metabolic panel to the likely acid-base pattern and helps identify whether there may be a mixed acid-base disorder. It also offers a convenient way to compare the lab result against the expected reference interval.
For example, if sodium is unchanged but bicarbonate drops because acid is building up, the calculation will often show anion gap elevation. If bicarbonate drops because it is being lost from the body and chloride rises to replace it, the gap may remain normal. That difference is central to clinical interpretation.
How Low Bicarbonate Influences the Anion Gap
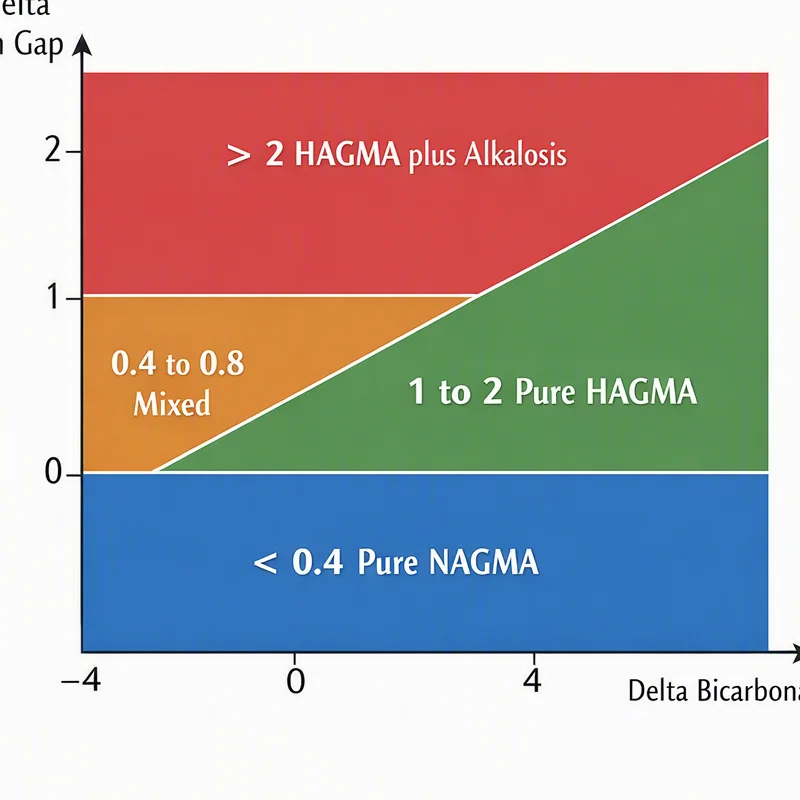
Decreased bicarbonate is common in metabolic acidosis, but the anion gap helps determine whether the problem is likely due to added acid or bicarbonate loss. In high anion gap metabolic acidosis, bicarbonate falls because it is used to buffer added acid, and the acid’s accompanying anions are not measured in the routine panel.
Classic causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, lactate behaves like an unmeasured anion. In ketoacidosis, ketone bodies increase and consume bicarbonate. In renal failure, the kidneys fail to remove acids effectively, so acid builds https://anion-gap-help865.rivetgarden.com/posts/anion-gap-calculator-for-clinical-judgement-support up and the anion gap rises.
These conditions all follow a common pattern: bicarbonate falls, and the “missing” negative charge appears as unmeasured anions. That is why bicarbonate is such a useful diagnostic clue. It does not just tell you that acid-base balance is disturbed; it helps indicate whether the body is keeping acid or depleting base.
In this setting, the low bicarbonate is part of the mechanism of the disorder, not just the result. As bicarbonate is consumed, the body’s compensatory response may include metabolic compensation through respiratory changes, which can be assessed with an arterial blood gas. The combined data help determine the final clinical interpretation.
Standard Anion Gap Metabolic Acidosis and Bicarbonate Loss
Not all low bicarbonate reading means a high anion gap. In normal anion gap metabolic acidosis, bicarbonate is lost from the body, but chloride rises to replace the lost negative charge. This creates a pattern of low bicarbonate with a preserved gap, often accompanied by hyperchloremia.
Frequent causes include diarrhea and renal tubular acidosis. With diarrhea, bicarbonate-rich intestinal fluid is lost, resulting in direct bicarbonate loss. In renal tubular acidosis, the kidneys fail to handle acid-base transport properly, and bicarbonate is either not reclaimed or acid is not excreted effectively.
Chloride plays a central role here. When bicarbonate decreases but the total charge balance must remain stable, chloride often increases in a chloride shift. The result is a non-anion gap pattern, sometimes called non-anion gap acidosis. Although the anion gap stays normal, the acid-base disorder is still clinically important.
For this reason bicarbonate should never be interpreted alone. A low bicarbonate with normal anion gap may point toward gastrointestinal loss, tubular dysfunction, or another cause of bicarbonate depletion. The lab pattern helps separate high-gap acid accumulation from normal-gap base loss.
Corrected Anion Gap and Albumin
Albumin is the primary unmeasured anion in a lot of patients. When albumin is low, the measured anion gap can appear falsely normal or only mildly elevated even when serious acid accumulation is present. That is why hypoalbuminemia can mask a clinically significant disorder.
The corrected anion gap adjusts for low albumin so that hidden unmeasured anions are not overlooked. Because albumin contributes negative charge to the serum, low albumin reduces the baseline gap. Correcting for this effect increases the accuracy of interpretation and helps reveal a masked high-gap state.
This matters most when a patient has low bicarbonate but the uncorrected anion gap seems normal. Without correction, an underlying high anion gap process could be missed. In practice, albumin correction is a practical step in the interpretation guide because it prevents underestimating acid burden.
Put simply, albumin influences the baseline. If albumin is low, the anion gap may need to be recalculated or corrected before deciding whether bicarbonate loss is due to a high-gap or normal-gap process. This is most important when the clinical picture suggests lactic acidosis, ketoacidosis, or renal failure.
How to Read Results In Steps
A thoughtful interpretation commences with the basic metabolic panel and may be extended with an arterial blood gas. The goal is to connect the lab pattern to the underlying acid-base disorder. A stepwise approach improves clinical interpretation and lowers the risk of missing a mixed acid-base disorder.
Begin by reviewing bicarbonate, sodium, chloride, and potassium on the electrolyte panel. Assess for low bicarbonate, abnormal chloride, and any major sodium shifts. These values shape the acid-base picture.
Next, calculate the anion gap using the standard formula or an Anion Gap Calculator. Contrast the result to the expected reference interval. A increased number suggests unmeasured acids or ions.
Step 3: Check albumin. If albumin is low, apply a corrected anion gap so that hypoalbuminemia does not hide the diagnosis.
Next, decide whether the pattern fits high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or another process. Consider whether bicarbonate has fallen because of acid accumulation, bicarbonate loss, or compensation for a respiratory disorder.
Step 5: Use the arterial blood gas to confirm pH and respiratory response. This is especially valuable when the result suggests a mixed disorder or when bicarbonate seems discordant with the clinical picture.
For example, a patient with low bicarbonate, an elevated gap, and increased lactate likely has lactic acidosis. Another patient with low bicarbonate, normal gap, and high chloride may have diarrhea-related bicarbonate loss or renal tubular acidosis. The lab pattern is the diagnostic clue, but the final interpretation should match the whole patient.
Key Questions About Bicarbonate and Anion Gap
Numerous questions come up when interpreting bicarbonate and the anion gap as a pair. The primary concern is whether a low bicarbonate always means the gap will be elevated. The answer is no. The pattern depends on the underlying acid-base mechanism, the electrolyte shifts involved, and whether albumin is normal.
It also helps to remember that the anion gap is not a direct measurement of a specific acid. It is a calculated value that estimates the presence of unmeasured ions. That means a normal gap does not exclude acid-base disease, and a high gap does not identify the exact cause by itself.
Respiratory and metabolic processes can overlap. For example, respiratory alkalosis may lower bicarbonate over time as the kidneys compensate, while metabolic alkalosis usually raises bicarbonate rather than lowers it. These patterns matter because they change how the serum chemistry should be read in context.
An electrolyte imbalance can also influence the result without representing a primary acid problem. That is why bicarbonate must be interpreted with sodium, chloride, potassium, albumin, and the rest of the clinical picture.
Does a Low Bicarbonate Always Mean a High Anion Gap?
No. Low bicarbonate can occur with anion gap elevation, but it can also occur with a normal gap. In high anion gap states, bicarbonate is consumed by added acids, and the gap increases because unmeasured anions accumulate. In normal-gap states, bicarbonate is often lost and replaced by chloride, so the gap stays stable.
That separation is crucial when assessing a possible mixed disorder. A low bicarbonate may suggest metabolic acidosis, respiratory compensation, or both. The anion gap helps sort out whether acid retention is present.
Can the Anion Gap Be Normal When Bicarbonate Is Low?
Yes. This is a classic pattern in hyperchloremic acidosis, also called non-anion gap acidosis. In this situation, bicarbonate falls but chloride rises, so the total calculated gap remains normal. Common examples include diarrhea and some forms of renal tubular acidosis.
Occasionally chloride replacement while treating may keep the gap normal while bicarbonate remains low. For that reason the same lab result can mean different results depending on timing, treatment, and clinical context. The best interpretation always considers the entire electrolyte pattern and, when needed, blood gas data.
FAQ
What is the role of bicarbonate in anion gap?
Bicarbonate is both a key buffer and a core part of the anion gap calculation. As part of the buffer system, it helps preserve acid-base balance and blood pH. In the formula, it is subtracted from sodium along with chloride, so a change in bicarbonate can increase or reduce the calculated gap depending on what is happening with the rest of the electrolytes.
Why does low bicarbonate happen in metabolic acidosis?
Low bicarbonate happens in metabolic acidosis because bicarbonate is used to handle excess acid. That consumption lowers serum bicarbonate and reduces buffering capacity. Depending on the cause, this may produce high anion gap metabolic acidosis, or it may occur with a normal anion gap if bicarbonate is being lost and chloride rises to take its place.
Can bicarbonate be low without an elevated anion gap?
Absolutely. Low bicarbonate can occur in normal anion gap metabolic acidosis, such as from diarrhea or renal tubular acidosis. In these cases, chloride usually increases, which preserves the gap normal. Low bicarbonate can also appear during compensation for other acid-base disorders, so the lab pattern must be evaluated carefully.
How does albumin change the anion gap calculation?
Albumin is an important unmeasured anion, so low albumin can make the measured anion gap look lower than it really is. This is why hypoalbuminemia may hide a genuine acid-base problem. A corrected anion gap adjusts for albumin and improves the detection of unmeasured anions in disorders such as lactic acidosis or ketoacidosis.
What conditions commonly cause a high anion gap?
Common causes of a high anion gap include lactic acidosis, ketoacidosis, and renal failure. These conditions lead to the accumulation of unmeasured anions and a decrease in bicarbonate. The anion gap clinical significance result is anion gap elevation, which is a key diagnostic clue in the evaluation of metabolic acidosis and other acid-base disorders.